# Model Updates in Medical Device Services Need a Joint Release Decision

A Management Method for Device Relevant Supplier Change

Author: Phil Hatch
Publisher: Akholi
Paper ID: AAO-079
Published: October 23, 2026
Language: en
Canonical: https://akholi.com/papers/model-updates-in-medical-device-services-need-a-joint-release-decision/
Audience: Medical-device outsourcing manager, supplier quality lead, regulatory operations manager

Medical-device service managers should assess provider model updates against the accepted device function, evidence, and applicable change pathway. An upstream improvement is not automatic permission to deploy a changed clinical service.

<h2 id="section-1">Identify the Device Relevant Change</h2>
<p>The service manager should establish whether an upstream model, tool, data, or configuration update affects the medical-device function or associated service. The supplier’s release label does not decide the regulatory or clinical significance. Start from intended use, affected users, performance, and patient consequence.</p>
<p>FDA explains that an authorized predetermined change control plan <a href="https://www.fda.gov/medical-devices/premarket-submissions-selecting-and-preparing-correct-submission/predetermined-change-control-plans">covers specified modifications implemented in accordance with that plan.</a><sup id="ref-1"><a href="#note-1" aria-label="Note 1">1</a></sup> It is not blanket approval for arbitrary model updates or changed intended use. The manager should confirm the actual device and authorized scope with qualified regulatory owners.</p>
<p>For a hypothetical diagnostic-support service, a new foundation model may change output behavior even if the customer interface remains the same. The manager should identify what evidence is affected and whether the deployed configuration remains within the accepted function and applicable change process.</p>
<h2 id="section-2">Connect Upstream Notice to Local Assessment</h2>
<p>The provider should describe the proposed change, implementation timing, affected components, known limitations, and available options. The buyer needs sufficient time and evidence to assess its own responsibilities. A notice received after automatic deployment cannot support a prior release decision.</p>
<p>The <a href="https://akholi.com/outsourcing-2026-agentic-ai-tier-1-banks/part-3-governance-oversight-control/">study</a>’s reported downstream dependency <a href="https://akholi.com/outsourcing-2026-agentic-ai-tier-1-banks/part-2-five-failure-categories/">and governance-function gaps identify a change-management mechanism to test.</a><sup id="ref-2"><a href="#note-2" aria-label="Note 2">2</a></sup> They do not establish medical-device noncompliance. The relevant question is whether the device organization can govern a consequential supplier change before it affects patients.</p>
<p>Keep the accepted configuration and evidence accessible. A model version name alone may omit instructions, retrieval data, tool access, and human review. The assessment should identify which parts of the assembled service change and how those differences can affect the intended clinical result.</p>
<h2 id="section-3">Use a Joint Device Change Record</h2>
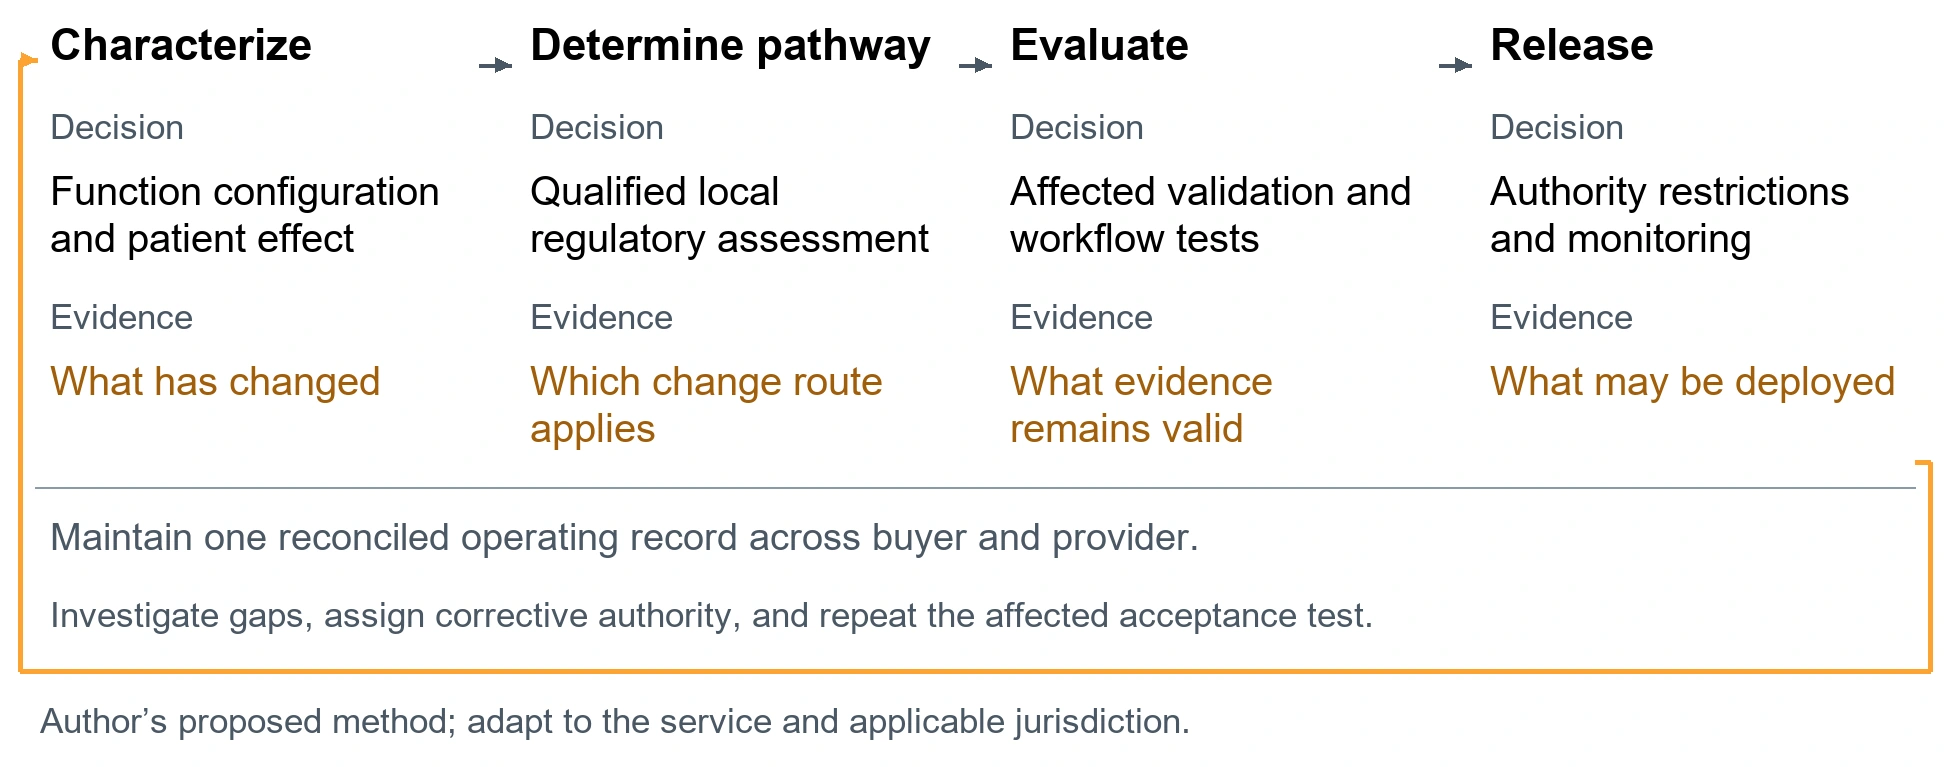
<p>Figure 1 proposes four decisions: characterize the change, determine the applicable pathway, generate relevant evidence, and authorize controlled release. Assign manufacturer, provider, and deploying-organization responsibilities according to their actual roles rather than assuming every party has the same duty.</p>
<p>FDA’s final PCCP guidance describes <a href="https://www.fda.gov/regulatory-information/search-fda-guidance-documents/marketing-submission-recommendations-predetermined-change-control-plan-artificial-intelligence">planned modifications, development and validation methods, and impact assessment.</a><sup id="ref-3"><a href="#note-3" aria-label="Note 3">3</a></sup> This US guidance should be applied within its stated device scope. Other jurisdictions require their own assessment of the applicable rules and evidence.</p>
<p>Include human factors, clinical workflow, failure handling, and consequential interactions with other systems where relevant. Test the changed service under representative conditions. A favorable generic model benchmark does not establish unchanged safety or effectiveness for the device’s intended use.</p>
<figure><img loading="lazy" src="https://akholi.com/wp-content/uploads/2026/10/079-f1.webp" width="1950" height="767" alt="The joint device change record. Characterize. Decision: Function configuration and patient effect. Evidence: What has changed. Determine pathway. Decision: Qualified local regulatory assessment. Evidence: Which change route applies. Evaluate. Decision: Affected validation and workflow tests. Evidence: What evidence remains valid. Release. Decision: Authority restrictions and monitoring. Evidence: What may be deployed. Maintain one reconciled operating record across buyer and provider.. Investigate gaps, assign corrective authority, and repeat the affected acceptance test.. Author’s proposed method; adapt to the service and applicable jurisdiction."><figcaption>Figure 1. The joint device change record<small><a href="https://akholi.com/outsourcing-2026-agentic-ai-tier-1-banks/">Phil Hatch, proposed framework developed for this paper.</a></small></figcaption></figure>
<h2 id="section-4">Prepare for Restricted Operation and Recovery</h2>
<p>EU, UK, Swiss, US, and other medical-device and healthcare requirements differ. Regulatory, quality, clinical, privacy, and technical owners should document local conclusions. Do not represent a future policy proposal, sandbox, or internal acceptance as an authorization already in force.</p>
<p>Agree whether the provider can delay, pin, restrict, or reverse the update. If it cannot preserve the old configuration, identify the consequence before relying on that option. A rollback also needs assessment of actions already taken and records produced by the changed service.</p>
<p>Plan communication to affected operators and users. The deployment record should state what changed, relevant limitations, required training, monitoring, and escalation. A technically successful update can still create unsafe use if the people responsible for the service continue under obsolete assumptions.</p>
<h2 id="section-5">Release Only the Change the Evidence Supports</h2>
<p>A reasonable objection is that upstream changes occur too often for full reassessment. Use a proportionate, pre-agreed classification method and reusable evidence. Reserve extensive work for consequential changes, while documenting why a smaller change remains within the accepted boundary.</p>
<p>Before release, confirm the actual configuration, required approvals, affected validation, operating restrictions, and monitoring plan. After release, review relevant performance and safety signals and reconcile any changed cases. Close the change only when the accepted deployment and actual service agree.</p>
<p>The manager should treat a device-relevant supplier update as a joint release decision. Useful innovation depends on controlled iteration. The acceptance question is whether the changed clinical service remains justified by evidence and the applicable pathway, not whether the provider calls the model better.</p>
<h2 id="section-6">Evidence and Source Note</h2>
<p>The study is a nonrepresentative cross-section of 850 vendor delivery-team <a href="https://akholi.com/outsourcing-2026-agentic-ai-tier-1-banks/introduction/">respondents</a> on 150 engagements serving Tier 1 financial institutions, collected during January–June 2026. Neither banks nor vendors corroborated the accounts. It establishes reported experience, not causation, legal breach, or market prevalence. Its application here is a mechanism to investigate, not an estimate of conditions in other industries. The author-supplied version 1.8.2 is dated November 1, 2026 and is cited as a forthcoming manuscript consulted October 23, 2026.<sup id="ref-4"><a href="#note-4" aria-label="Note 4">4</a></sup></p>
<p>This is an analytical decision paper based on the supplied study and selected primary public sources checked through October 23, 2026. The original contribution is a joint device-change record connecting upstream model releases to device-specific evidence, local pathways, and operating acceptance. The proposed method has not been independently validated. Legal requirements depend on the entity, activity, jurisdiction, and effective provisions; supervisory observations, research, and professional commentary have distinct authority.</p>
<h2 id="notes">Notes</h2><ol class="akp-notes"><li id="note-1">US Food and Drug Administration, “Predetermined Change Control Plans,” US Food and Drug Administration, accessed October 23, 2026, PCCP scope, authorized modifications, and impact assessment, <a href="https://www.fda.gov/medical-devices/premarket-submissions-selecting-and-preparing-correct-submission/predetermined-change-control-plans">https://www.fda.gov/medical-devices/premarket-submissions-selecting-and-preparing-correct-submission/predetermined-change-control-plans</a>. <a href="#ref-1" aria-label="Return to note 1">↩</a></li><li id="note-2">Phil Hatch, <i>Agentic AI Outsourcing at Tier 1 Financial Institutions: Full Study Report</i>, version 1.8.2 (Akholi, forthcoming manuscript dated November 1, 2026), Part 3, Third-Party Ecosystem, sec. 6.1, “Mapping of Third and Fourth Party Dependencies,” indicator C196, <a href="https://doi.org/10.2139/ssrn.7164559">https://doi.org/10.2139/ssrn.7164559</a>; Hatch, <i>Agentic AI Outsourcing</i>, Part 2, secs. 4.2–4.3, “Human Review Capacity Against Agent Output Volume” and “Routine Approval of Agent Output at Human Review Points”. <a href="#ref-2" aria-label="Return to note 2">↩</a></li><li id="note-3">US Food and Drug Administration, “Marketing Submission Recommendations for a Predetermined Change Control Plan for Artificial Intelligence-Enabled Device Software Functions,” US Food and Drug Administration, August 2025, official final guidance summary on planned modifications and assessment, <a href="https://www.fda.gov/regulatory-information/search-fda-guidance-documents/marketing-submission-recommendations-predetermined-change-control-plan-artificial-intelligence">https://www.fda.gov/regulatory-information/search-fda-guidance-documents/marketing-submission-recommendations-predetermined-change-control-plan-artificial-intelligence</a>. <a href="#ref-3" aria-label="Return to note 3">↩</a></li><li id="note-4">Hatch, <i>Agentic AI Outsourcing</i>, Introduction, “Executive Summary” and “Evidentiary Basis and Its Limits”. <a href="#ref-4" aria-label="Return to note 4">↩</a></li></ol>
<h2 id="bibliography">Bibliography</h2><ul class="akp-bibliography"><li>Hatch, Phil. <i>Agentic AI Outsourcing at Tier 1 Financial Institutions: Full Study Report</i>. Version 1.8.2. Akholi. Forthcoming manuscript dated November 1, 2026. Author-supplied manuscript consulted October 23, 2026. <a href="https://doi.org/10.2139/ssrn.7164559">https://doi.org/10.2139/ssrn.7164559</a>.</li><li>US Food and Drug Administration. “Marketing Submission Recommendations for a Predetermined Change Control Plan for Artificial Intelligence-Enabled Device Software Functions.” US Food and Drug Administration. August 2025. <a href="https://www.fda.gov/regulatory-information/search-fda-guidance-documents/marketing-submission-recommendations-predetermined-change-control-plan-artificial-intelligence">https://www.fda.gov/regulatory-information/search-fda-guidance-documents/marketing-submission-recommendations-predetermined-change-control-plan-artificial-intelligence</a>.</li><li>US Food and Drug Administration. “Predetermined Change Control Plans.” US Food and Drug Administration. Accessed October 23, 2026. <a href="https://www.fda.gov/medical-devices/premarket-submissions-selecting-and-preparing-correct-submission/predetermined-change-control-plans">https://www.fda.gov/medical-devices/premarket-submissions-selecting-and-preparing-correct-submission/predetermined-change-control-plans</a>.</li></ul>
